

Blog › Ingredients
Nano-Hydroxyapatite vs Fluoride: What the Research Actually Says
n-HA is legitimate — for the right patient. Two questions and we'll tell you whether you're a fluoride case or an n-HA case, with the research below.

I review every prescription order myself — same judgement I'd use with you in the chair.
Dr. Azar Sona Saeidi, DMDPracticing dentist · Soothing Dental, San Francisco
Find your prescription toothpaste
Two questions · about 20 seconds
Which of these sound like you?
Tap all that apply — these are the groups who genuinely benefit from 5,000 ppm
Uses Dr. Saeidi's own decision rules
Anything else we should factor in?
Tap any that apply — this is what separates the four brands: pH, added minerals, taste, price
Opens store.soothing.dental — our online store, same practice. A licensed dentist reviews the order before it ships.
Call (415) 630-6534 or book a consultation.
The short version
- For high-risk adults, the evidence still favours fluoride at 5,000 ppm.
- For low-risk adults and young children, n-HA is a defensible choice.
- They are not mutually exclusive — some patients alternate.
- Sensitivity relief is where n-HA performs best in the literature.
For seventy years, fluoride has held the title of gold-standard remineralizer in modern dentistry. Currently, that consensus is being challenged — politely, scientifically, and with growing evidence — by nano-hydroxyapatite (n-HA). The hydroxyapatite vs fluoride debate is no longer fringe. It's showing up in peer-reviewed journals, dental school curricula, and patient questions during routine cleanings.
I'm Dr. Sona Saeidi at Soothing Dental in San Francisco. Here's where the actual research stands, where the marketing gets ahead of the data, and how I'm thinking about hydroxyapatite for my own patients
A Brief History of Hydroxyapatite in Dentistry
Hydroxyapatite is the mineral your teeth and bones are made of. The chemistry is roughly Ca10(PO4)6(OH)2, and it's been studied as a synthetic dental material since the 1970s. Japan led the early work — NASA had pioneered hydroxyapatite for bone repair in astronauts after spaceflight, and Japanese researchers adapted the technology for tooth remineralization. The first n-HA toothpaste, Apagard, hit Japanese pharmacy shelves in 1980 and has been sold there continuously since.
Outside Japan, hydroxyapatite stayed niche until the late 2010s. The shift came from two directions. First, fluoride skepticism — partly evidence-based concerns about systemic exposure, partly social-media-driven distrust. Second, real product innovation. RiseWell, Boka, and Davids brought hydroxyapatite to American shelves with clean-label branding that resonated with consumers tired of synthetic toothpaste ingredients.
The honest split: risk level decides, not marketing.
Hydroxyapatite vs Fluoride: How Each One Actually Works
To make sense of the hydroxyapatite vs fluoride comparison, you have to understand that the two molecules don't just deliver different ingredients — they work through fundamentally different mechanisms.
The mechanisms are genuinely different, and that matters for the comparison.
Fluoride's mechanism
Fluoride works by replacing the hydroxyl group in your enamel's hydroxyapatite, creating fluorapatite. Fluorapatite is more acid-resistant than the native crystal — it dissolves at a lower pH (around 4.5) versus hydroxyapatite (around 5.5). When acid attacks your enamel, fluoride-strengthened crystal holds up longer. Fluoride also has direct antibacterial effects against Streptococcus mutans, the primary cavity organism. This is the dual-action advantage that has kept fluoride in front for decades.
Hydroxyapatite's mechanism
Synthetic n-HA particles bond directly to the tooth surface, filling micro-pits and demineralized zones with the exact mineral your enamel is built from. There's no ion-exchange chemistry; the crystal simply integrates. Imagine patching drywall with the same drywall material rather than spackle. Hydroxyapatite doesn't have direct antibacterial action — it's structural rather than pharmacological. This is its honest weakness against fluoride: it remineralizes well but doesn't suppress the bacteria producing the acid.
Not sure which one you need? Two questions, about twenty seconds, and Dr. Saeidi's own decision rules point you to one — with the reason.
Find my matchClinical Evidence: What the Research Actually Says
The hydroxyapatite vs fluoride debate has matured enough that we have real head-to-head trials to draw on, not just mechanism studies.
The studies I'd point patients to cluster around a few themes.
Head-to-head trials
Several randomized trials have compared 1,450 ppm fluoride toothpaste against 10% n-HA toothpaste in healthy adults. The largest, a 2019 trial published in Frontiers in Public Health, followed about 170 adults for 18 months. Cavity rates were statistically equivalent between groups — neither product was meaningfully better than the other in low-to-moderate-risk adults. A 2020 systematic review reached a similar conclusion: in low-risk populations, n-HA is non-inferior to fluoride at over-the-counter concentrations.
Where the data thins is at prescription-strength fluoride (5,000 ppm) vs n-HA. There aren't yet head-to-head trials at that level. The clinical reality is that 5,000 ppm fluoride drives remineralization at a rate n-HA hasn't been shown to match in high-risk adults.
Pediatric studies
This is where n-HA's case strengthens. Children under 6 face fluoride dosing concerns because they often swallow toothpaste, and excessive systemic fluoride during enamel development can cause fluorosis (white streaks or pitting). N-HA carries no such concern — swallowed n-HA is biologically inert. A 2018 pediatric trial out of Germany found 10% n-HA toothpaste prevented cavities at rates comparable to fluoride toothpaste in young children, with no fluorosis risk. For families specifically worried about fluoride exposure in young kids, this is a credible alternative. CariFree Gel 1100 Kids remains our default fluoride option for children, but the n-HA conversation is real.
White-spot lesions and post-orthodontic care
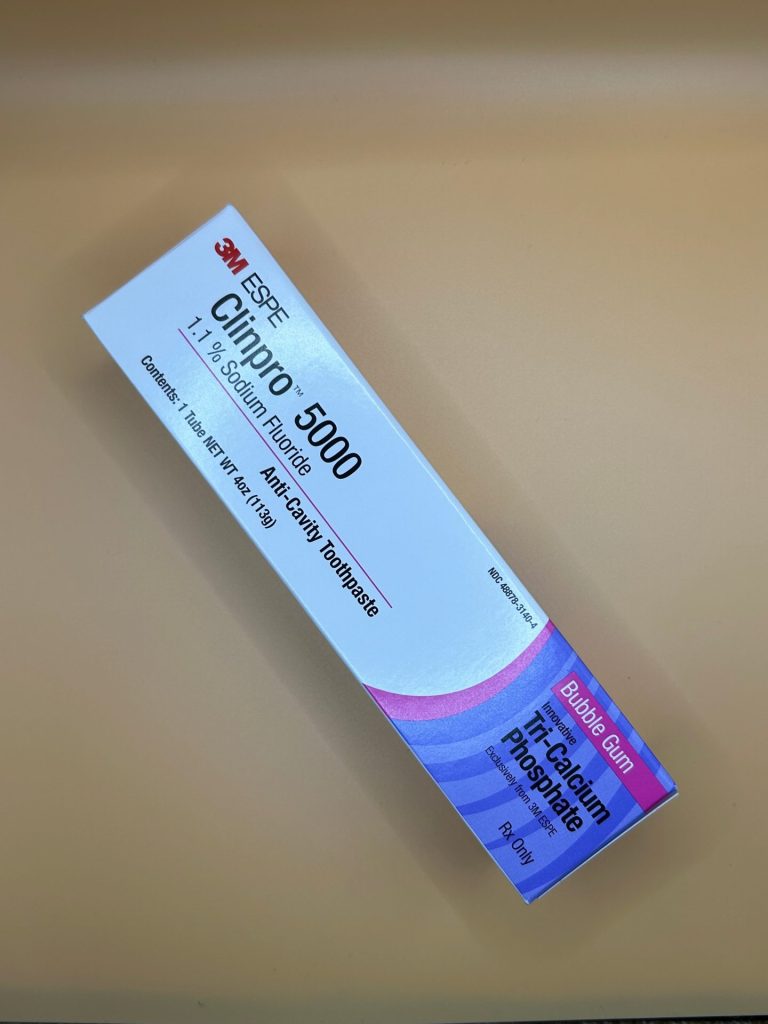
Mixed evidence here. Some studies show n-HA outperforming fluoride for early lesion reversal because the structural delivery directly fills the demineralized zone. Other studies favor fluoride. The honest answer is that for active white-spot lesions, the calcium-phosphate-fluoride combination found in products like Clinpro 5000 likely beats either pure-fluoride or pure-n-HA monotherapy.
Neither is a marketing story. They simply have different evidence in different jobs.
Sensitivity Relief
One area where n-HA performs well is tooth sensitivity. The particles physically occlude exposed dentinal tubules, reducing fluid flow that triggers nerve pain. Patients with sensitivity often report relief within 1 to 2 weeks of switching to n-HA, comparable to or better than potassium nitrate (the active in Sensodyne). For patients whose primary complaint is sensitivity rather than cavity risk, n-HA is a defensible first move.
Who Should Use Which?
Stick with fluoride if you:
- Have moderate-to-high cavity risk
- Have a recent history of cavities (two or more in three years)
- Have dry mouth or take cariogenic medications
- Have orthodontic appliances or recent ortho
- Have exposed root surfaces
- Live in a community with already-fluoridated water (the synergy works)
Hydroxyapatite is reasonable if you:
- Are low-to-moderate cavity risk
- Have specific concerns about systemic fluoride exposure
- Have young children where fluoride-swallowing is a worry
- Are primarily managing tooth sensitivity
- Are pregnant and want to minimize total fluoride load (though topical fluoride is considered safe)
Brand Availability
The mainstream n-HA brands worth knowing are RiseWell (the most clinically-cited U.S. brand), Apagard (the original Japanese brand), Boka Ela Mint (clean-label and accessible), and Davids Premium. Concentrations range from 5% to 15% n-HA. The 10% range is the sweet spot most studies have used. Avoid products that vaguely claim "hydroxyapatite" without specifying concentration — those are usually subtherapeutic.
For prescription strength fluoride alternatives, see our complete guide to prescription strength toothpaste. For a direct comparison of two prescription fluorides, see CariFree Pro Gel 5000 vs Clinpro 5000.
A Note on Combination Use
You don't have to pick. Some patients alternate — fluoride toothpaste in the morning, n-HA at night. Others use n-HA as a daily paste with fluoride mouthrinse for the antibacterial benefit. There's no clinical evidence that combining them harms efficacy, and there's some theoretical support for the synergy. If you want both benefits, alternating is reasonable.
Practical Concerns: Cost, Availability, and Taste
The hydroxyapatite vs fluoride question often comes down to practical considerations once the clinical case is settled.
Cost
N-HA toothpastes typically run $15 to $25 per tube — comparable to over-the-counter fluoride pastes and noticeably cheaper than 5,000 ppm prescription fluoride. For a low-risk adult choosing between OTC fluoride and OTC n-HA, cost is a wash. For a high-risk adult comparing n-HA to prescription fluoride, n-HA looks cheaper on the shelf but lacks the clinical evidence at the equivalent strength tier.
Availability
RiseWell and Boka are now stocked at most major U.S. retailers, including Whole Foods, Target, and increasingly Amazon. Apagard requires online ordering for most U.S. customers. Prescription fluoride still requires the prescription pathway. If frictionless purchase matters to you, n-HA wins on convenience.
Taste and texture
N-HA toothpastes generally taste cleaner than prescription fluoride pastes, which can have an artificial mint flavor. RiseWell's strawberry option is particularly popular with kids who refuse traditional toothpaste. For adherence-driven decisions — especially in households with picky brushers — taste matters more than the abstract clinical comparison.
What About Sensodyne and Other Sensitivity-Specific Products?
Sensodyne and similar potassium-nitrate-based products work on a different mechanism: they desensitize nerves rather than remineralize enamel. They are not direct competitors to either fluoride or hydroxyapatite, even though all three appear on the same shelf. If sensitivity is your primary issue and cavity risk is low, Sensodyne is a defensible pick. If you have both sensitivity and cavity risk, n-HA addresses both simultaneously while Sensodyne addresses only the symptom.
Not sure which one you need? Two questions, about twenty seconds, and Dr. Saeidi's own decision rules point you to one — with the reason.
Find my matchThe Honest Take
Fluoride is not obsolete. The evidence base is broader, deeper, and more replicated than n-HA's, and at prescription strengths, fluoride still wins for high-risk adults. But hydroxyapatite has earned a legitimate seat at the table, particularly for low-risk adults, sensitivity sufferers, and pediatric cases where fluorosis is a real concern.
What I tell patients: pick based on your actual risk profile, not on social-media takes. If you're a 35-year-old adult with no cavities in five years, n-HA is fine. If you're managing recurrent decay, dry mouth, or recession, prescription fluoride remains the right tool, and you can order it online with a complimentary Rx review.
If you're not sure where you fall, book a checkup — risk assessment is exactly what cleanings are for.
Related products and pages
About Dr. Sona Saeidi, DMD
Cofounder of Soothing Dental in San Francisco's Financial District. DMD magna cum laude, Boston University Goldman School of Dental Medicine. Practicing in California since 2011 (license #60566). Member of the American Dental Association, California Dental Association, and San Francisco Dental Society.

This page is educational and is not a diagnosis. Products sold through Soothing Dental may require a prescription; eligibility is confirmed through a brief telehealth screen at checkout.